← 返回线下交流 · 课件馆
HFS MVD Neuroanesthesia Teaching 面向康奈尔大学大一见习学生的中英双语课件 Bilingual course for a first-year Cornell student observer

Neuroanesthesia Observation

面肌痉挛微血管减压术全麻见习课 General Anesthesia Observation for Hemifacial Spasm MVD

用明天的病例讲清楚一条主线:面神经为什么会抽动,手术怎样解除血管压迫,麻醉医生怎样在全麻、气道安全、神经监测和苏醒质量之间保持平衡。 Use tomorrow's case to understand one clinical line: why the facial nerve twitches, how MVD relieves vascular compression, and how anesthesia balances airway safety, monitoring signals, and smooth emergence.

HFS 面肌痉挛 hemifacial spasm
MVD 微血管减压术 microvascular decompression
10 英文标识教学图 English-labeled figures
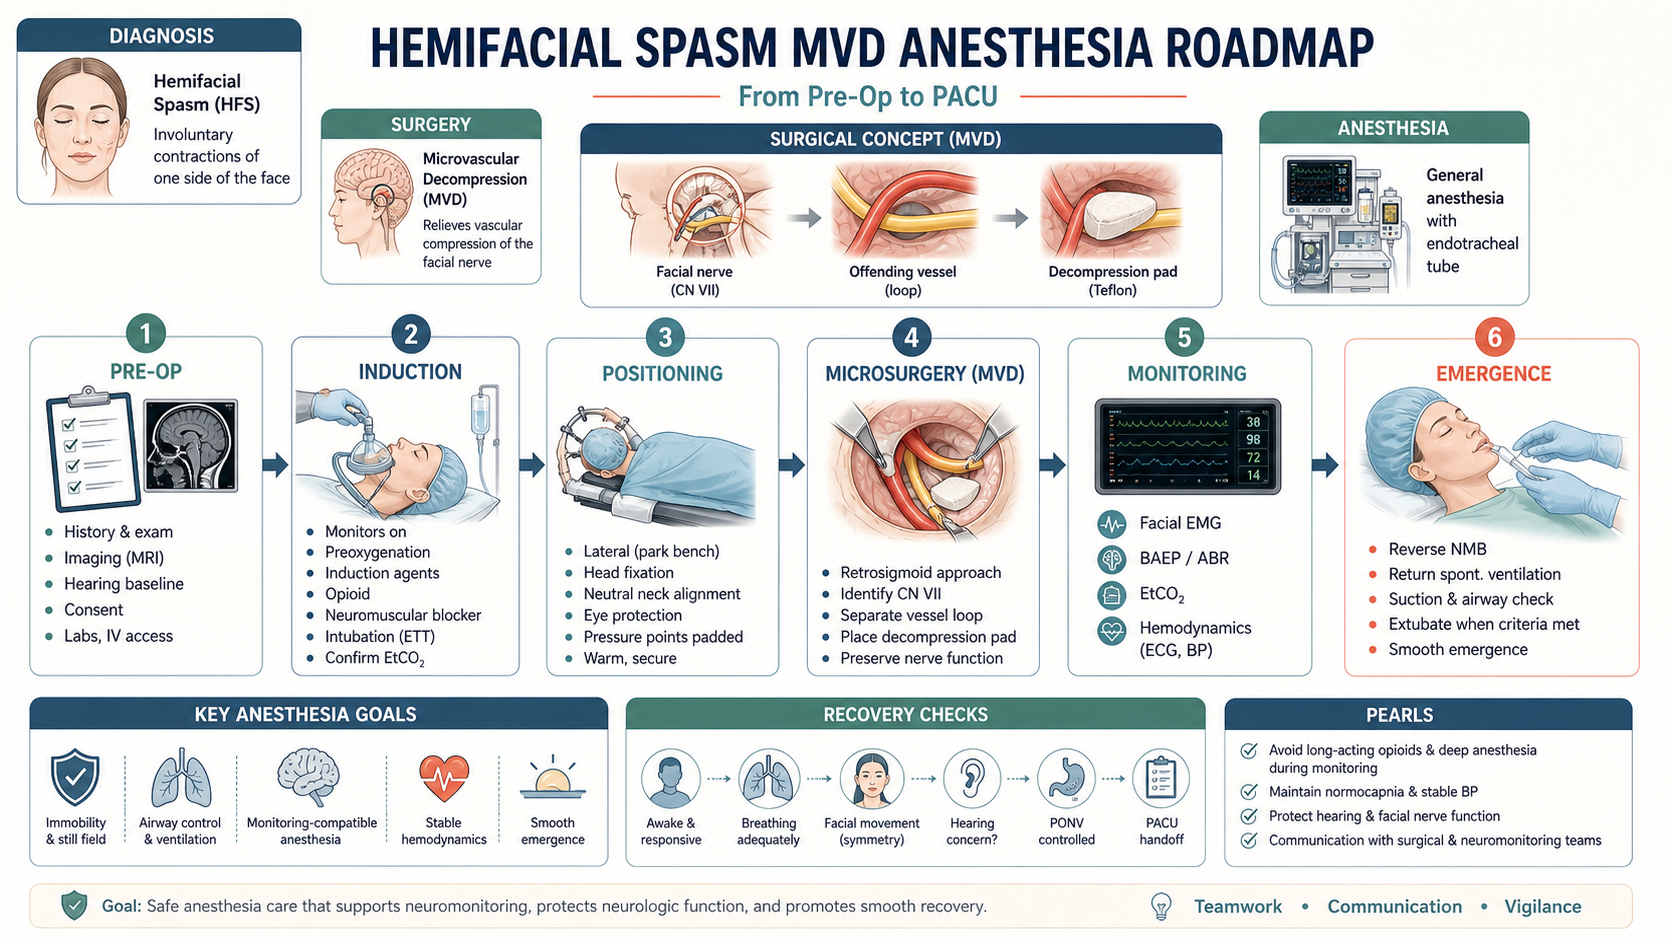
Hemifacial spasm MVD anesthesia roadmap
总览图把诊断、手术、全麻、神经监测和苏醒观察放在同一条路线里。 The roadmap connects diagnosis, surgery, general anesthesia, neurophysiological monitoring, and recovery checks.

Case Map

今日病例:从“脸抽动”看到“颅神经保护”Today's Case: From Facial Twitching to Cranial Nerve Protection

学生今天要看懂什么What the student should understand

这台手术不是简单地“把血管拿开”。对麻醉见习来说,更重要的是理解:患者为什么需要稳定全麻,为什么神经监测会影响麻醉用药,为什么苏醒时要特别平稳。

This case is not just moving a vessel away. For anesthesia observation, the key is understanding why stable general anesthesia is needed, why monitoring affects anesthetic choices, and why emergence must be smooth.
Hemifacial Spasm Microvascular Decompression General Anesthesia with ETT Facial EMG BAEP / ABR
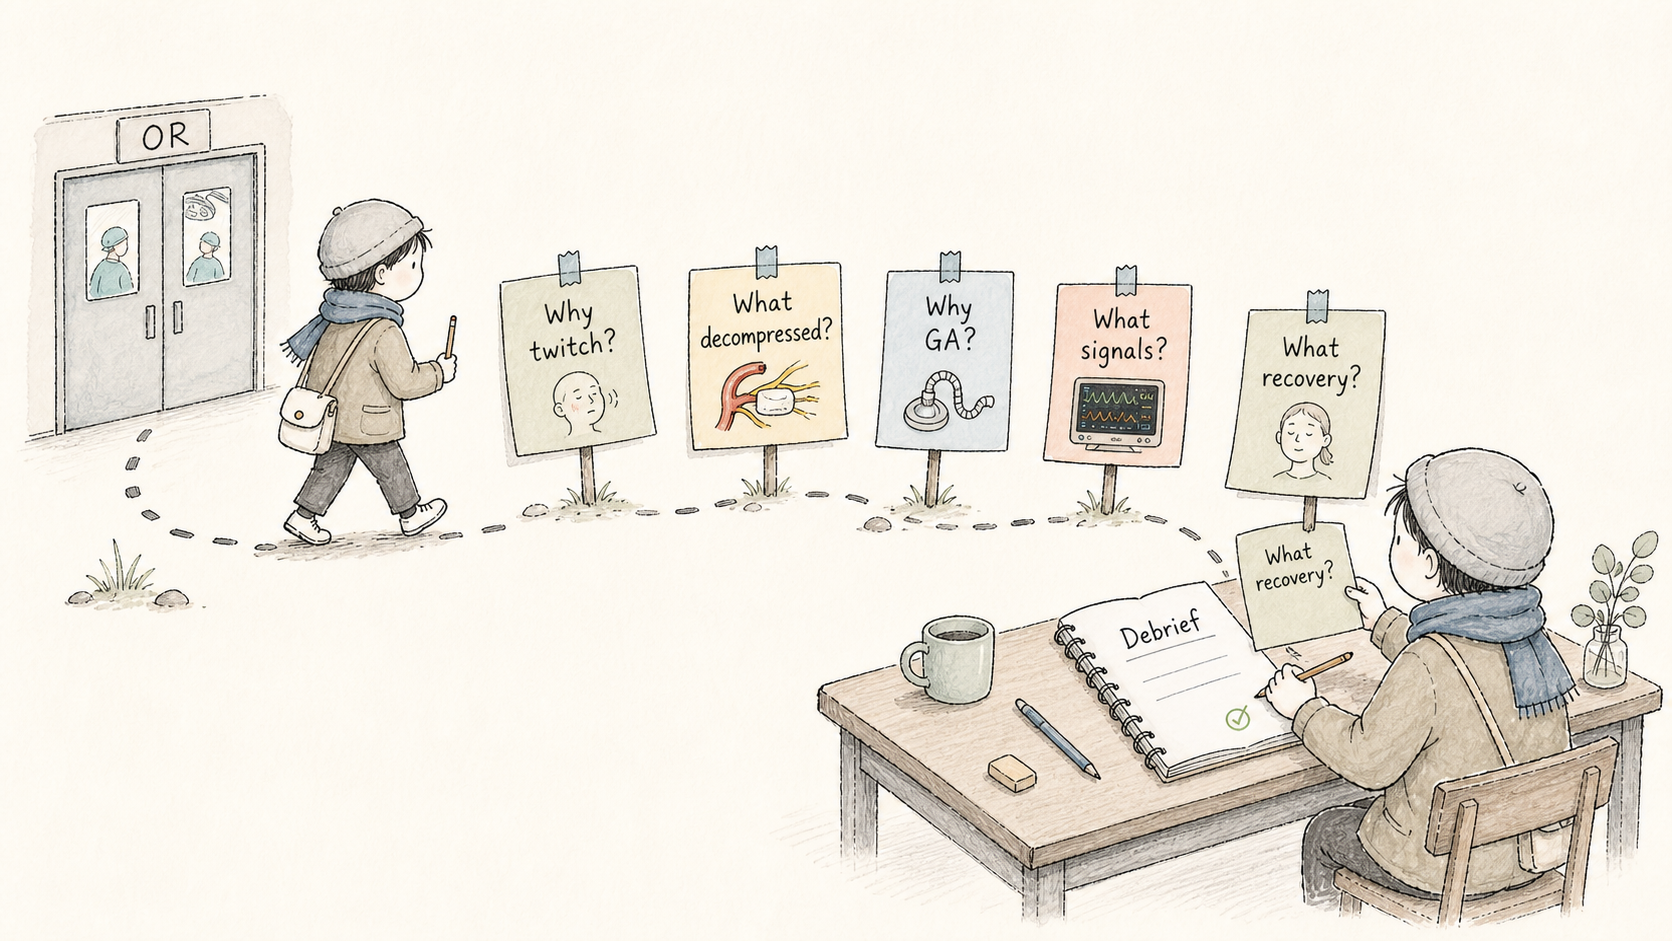
Debrief questions after MVD
这张图适合术后复盘:用五个问题把“看见”变成“理解”。 This figure supports the post-case debrief: five questions turn observation into reasoning.

Disease Mechanism

面肌痉挛:面神经被“持续敲门”Hemifacial Spasm: The Facial Nerve Is Being Irritated

面肌痉挛通常表现为一侧面部不自主抽动。一个常见机制是面神经在脑干附近受到血管压迫或刺激,异常放电传到面部肌肉,形成反复抽动。

Hemifacial spasm often presents as involuntary contractions on one side of the face. A common mechanism is vascular compression or irritation of the facial nerve near the brainstem, leading to abnormal firing and facial muscle twitching.
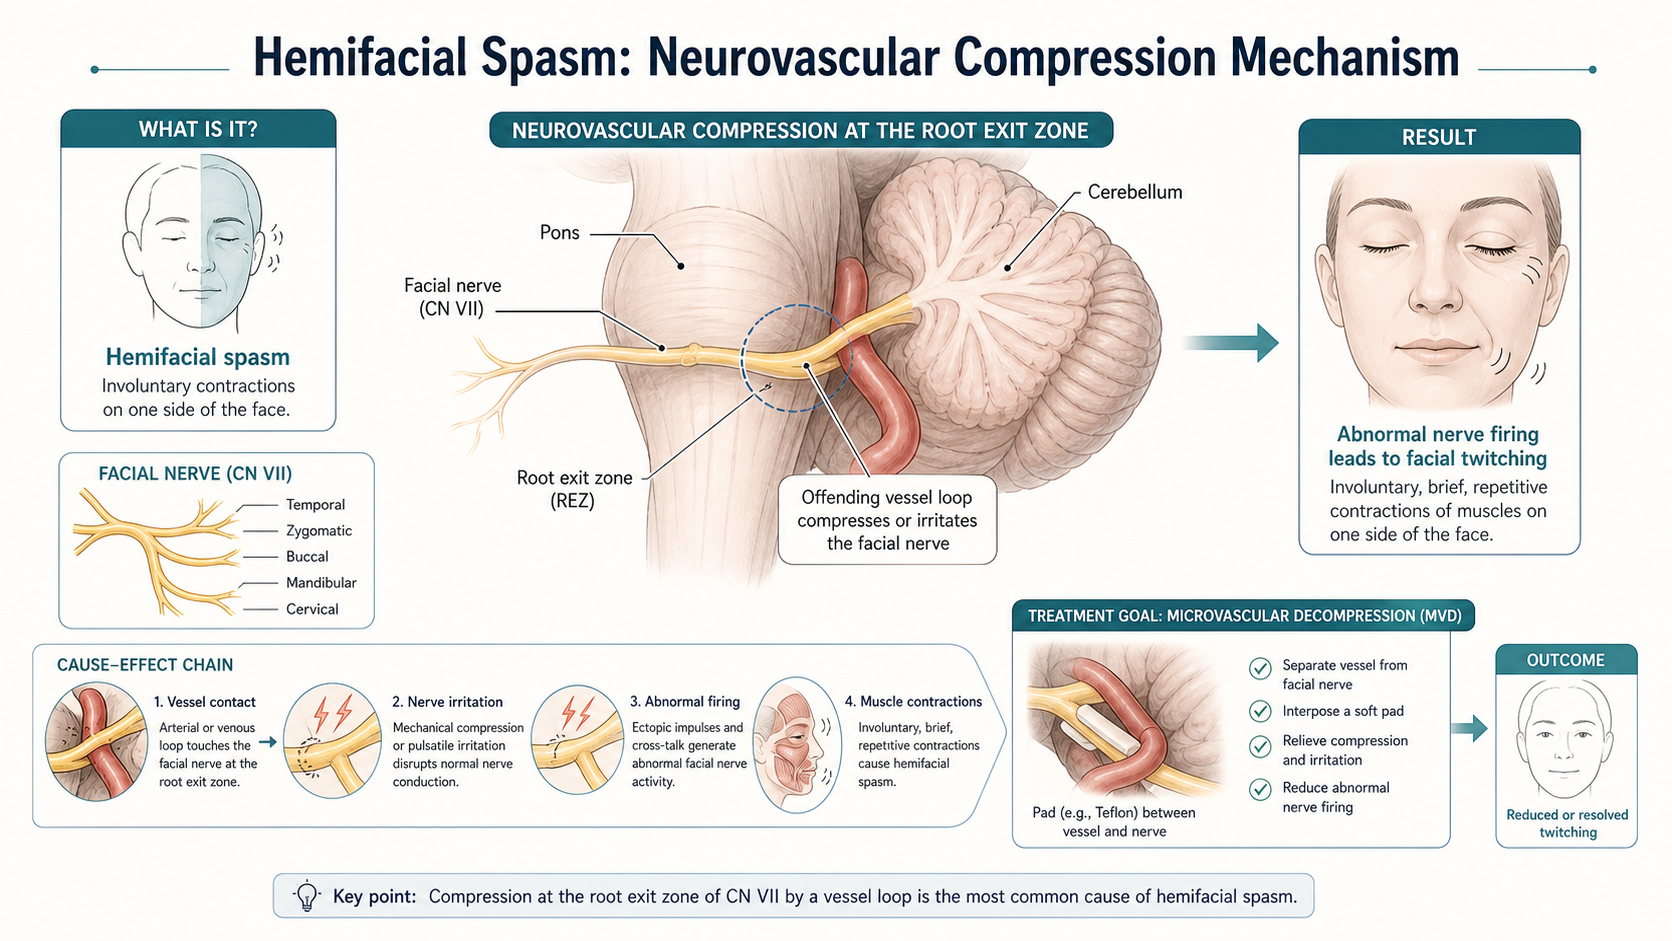
Hemifacial spasm neurovascular compression mechanism
讲解顺序:血管接触面神经 → 神经受刺激 → 异常放电 → 面部肌肉抽动。 Teaching sequence: vessel contacts facial nerve -> nerve irritation -> abnormal firing -> facial muscle contractions.
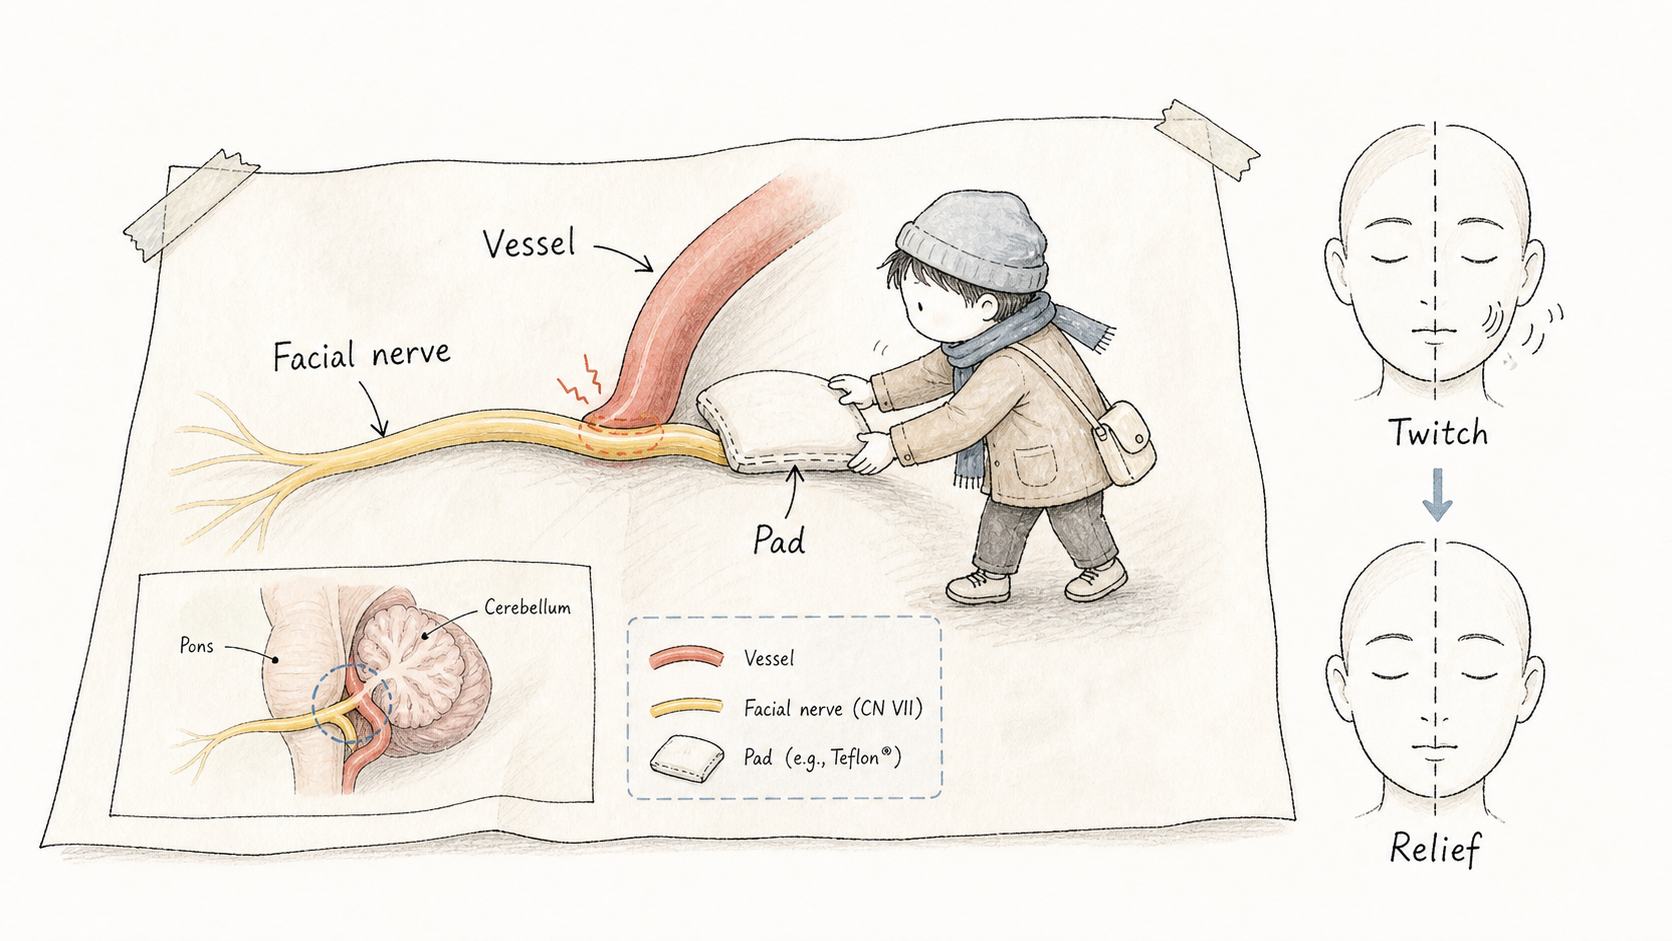
Hand-drawn vessel nerve separation
手绘图把“血管压迫神经”和“垫片隔开”讲得更生活化,适合给初学者打底。 The hand-drawn figure makes vessel-nerve compression and separation easier for a beginner to grasp.

Surgical Goal

MVD 做什么:解除压迫,而不是切断神经What MVD Does: Relieve Compression, Not Cut the Nerve

微血管减压术的核心是找到压迫面神经的责任血管,将血管从神经上移开,并用软垫把两者隔开。对学生来说,最重要的一句话是:手术目标是解除“血管-神经冲突”,同时保护面神经和听神经等邻近结构。

The core of MVD is identifying the offending vessel, moving it away from the facial nerve, and placing a soft pad between vessel and nerve. The key teaching line is: relieve the vessel-nerve conflict while protecting the facial nerve and nearby structures such as CN VIII.
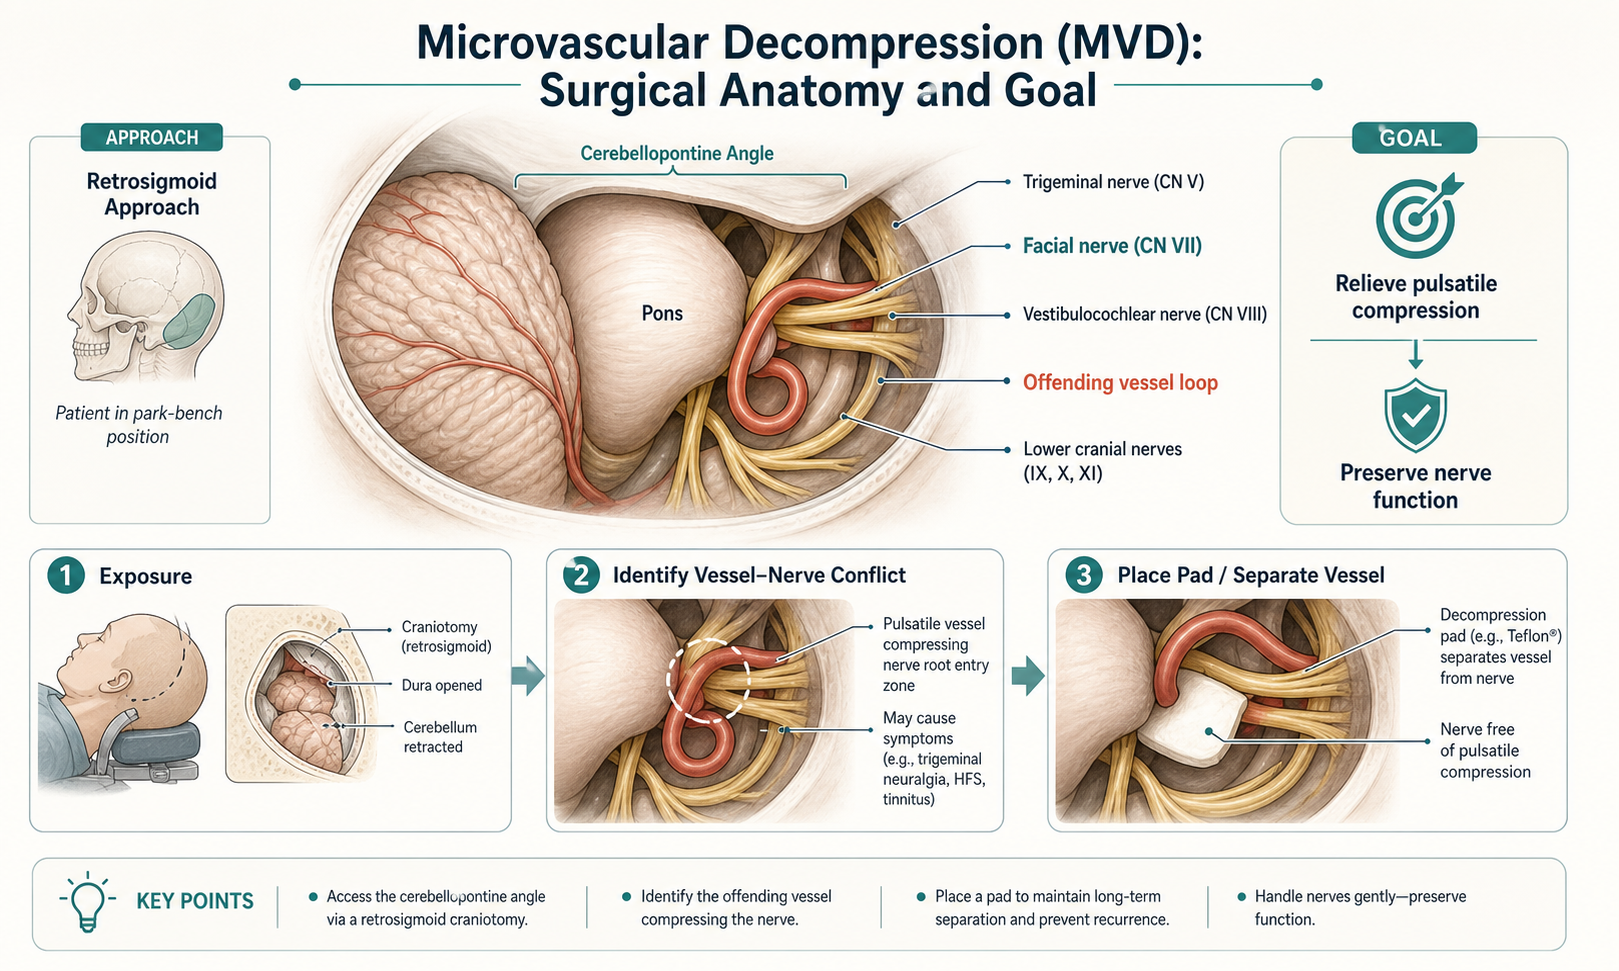
不要把 MVD 讲成“切掉抽动的神经”。它更像是把反复碰撞的两件东西轻轻分开。 Do not describe MVD as cutting the twitching nerve. It is more like gently separating two structures that keep colliding.
MVD surgical anatomy and goal
图中把后颅窝、脑干、面神经、听神经附近关系和垫片目标放在一起。 The figure connects posterior fossa anatomy, brainstem, facial nerve, nearby CN VIII, and the decompression pad.

Why General Anesthesia

为什么需要全身麻醉气管插管Why General Anesthesia with Endotracheal Intubation

这类后颅窝显微手术需要患者完全静止、头部固定、气道可靠、通气稳定,并且要为神经监测创造条件。全麻气管插管让麻醉医生能控制氧合、通气和二氧化碳,同时维持合适麻醉深度。

Posterior fossa microsurgery requires immobility, head fixation, a secure airway, stable ventilation, and conditions suitable for nerve monitoring. General anesthesia with an endotracheal tube allows control of oxygenation, ventilation, carbon dioxide, and anesthetic depth.
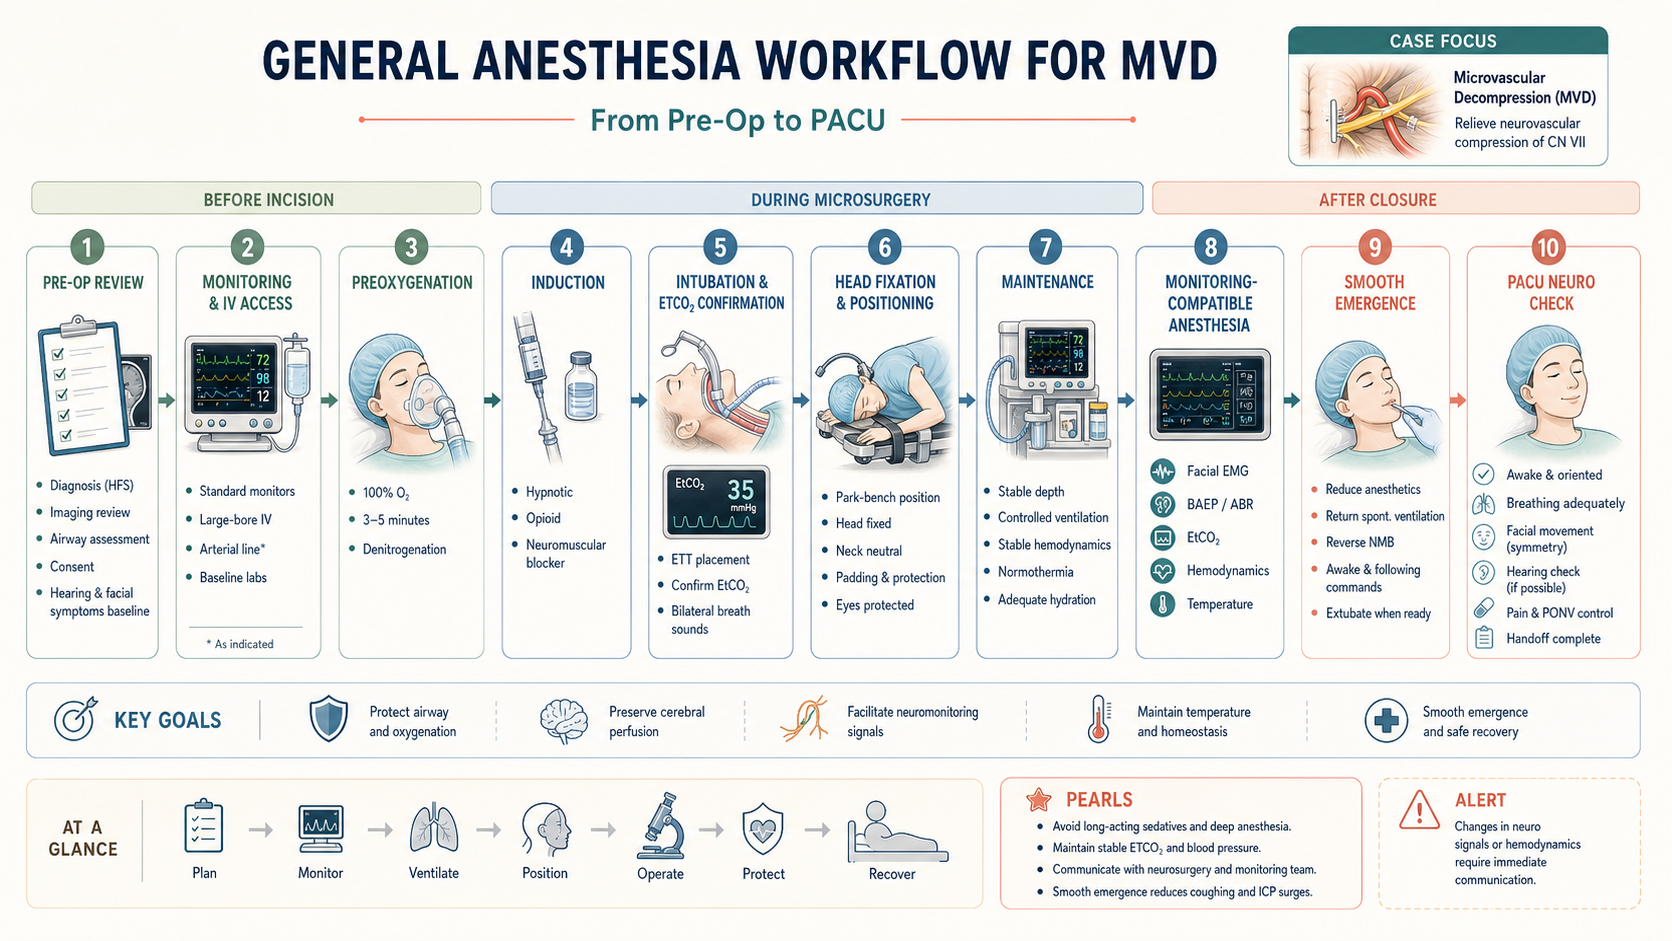
General anesthesia workflow for MVD
这张图适合术前讲全流程:诱导、插管、头部固定、维持、神经监测配合、平稳苏醒。 This timeline introduces induction, intubation, head fixation, maintenance, monitoring-compatible anesthesia, and smooth emergence.

Neurophysiological Monitoring

神经监测:手术团队的“早期报警系统”Neurophysiological Monitoring: The Team's Early Warning System

在 MVD 中,术中神经电生理监测帮助团队观察面神经和听觉通路相关信号。对初学者不必讲太深,只要知道:面肌肌电 `Facial EMG` 反映面神经相关肌肉活动;`BAEP/ABR` 用于观察听觉通路;信号质量会受麻醉、肌松、体温、灌注和团队沟通影响。

During MVD, intraoperative neurophysiological monitoring helps the team observe facial nerve and auditory pathway signals. For a beginner: Facial EMG reflects facial nerve-related muscle activity; BAEP/ABR observes auditory pathway function; signal quality can be affected by anesthesia, neuromuscular blockade, temperature, perfusion, and team communication.
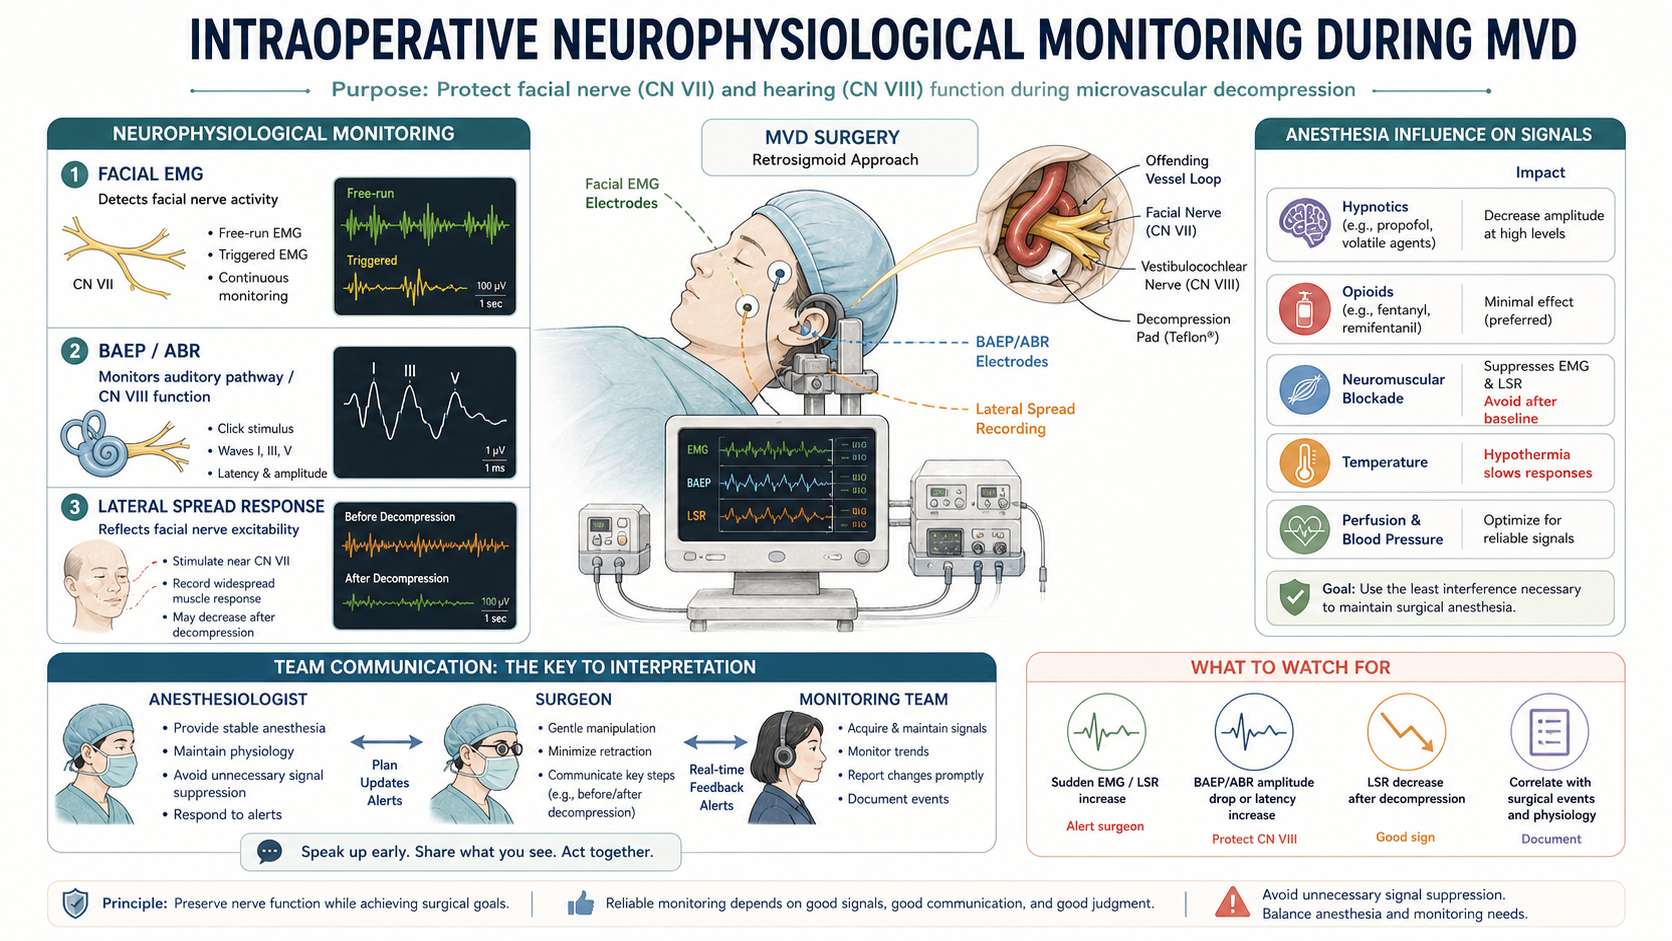
Intraoperative neurophysiological monitoring during MVD
让学生听懂三个词就够:Facial EMG、BAEP/ABR、signal quality。 For the student, three terms are enough to start: Facial EMG, BAEP/ABR, and signal quality.

Anesthesia-Monitoring Balance

麻醉难点:既要安全插管,也要保留监测信号The Anesthesia Challenge: Secure the Airway, Preserve Useful Signals

插管时常需要肌松,但面神经肌电监测需要肌肉反应可以被观察到。持续过深肌松可能让 EMG 信号不可靠。因此,这台手术很适合给学生讲“麻醉不是固定配方,而是和手术阶段、监测团队持续协调”。

Intubation often needs neuromuscular relaxation, but facial EMG monitoring requires detectable muscle responses. Continuous deep paralysis can reduce signal reliability. This case is ideal for teaching that anesthesia is not a fixed recipe; it is coordinated with surgical stages and the monitoring team.
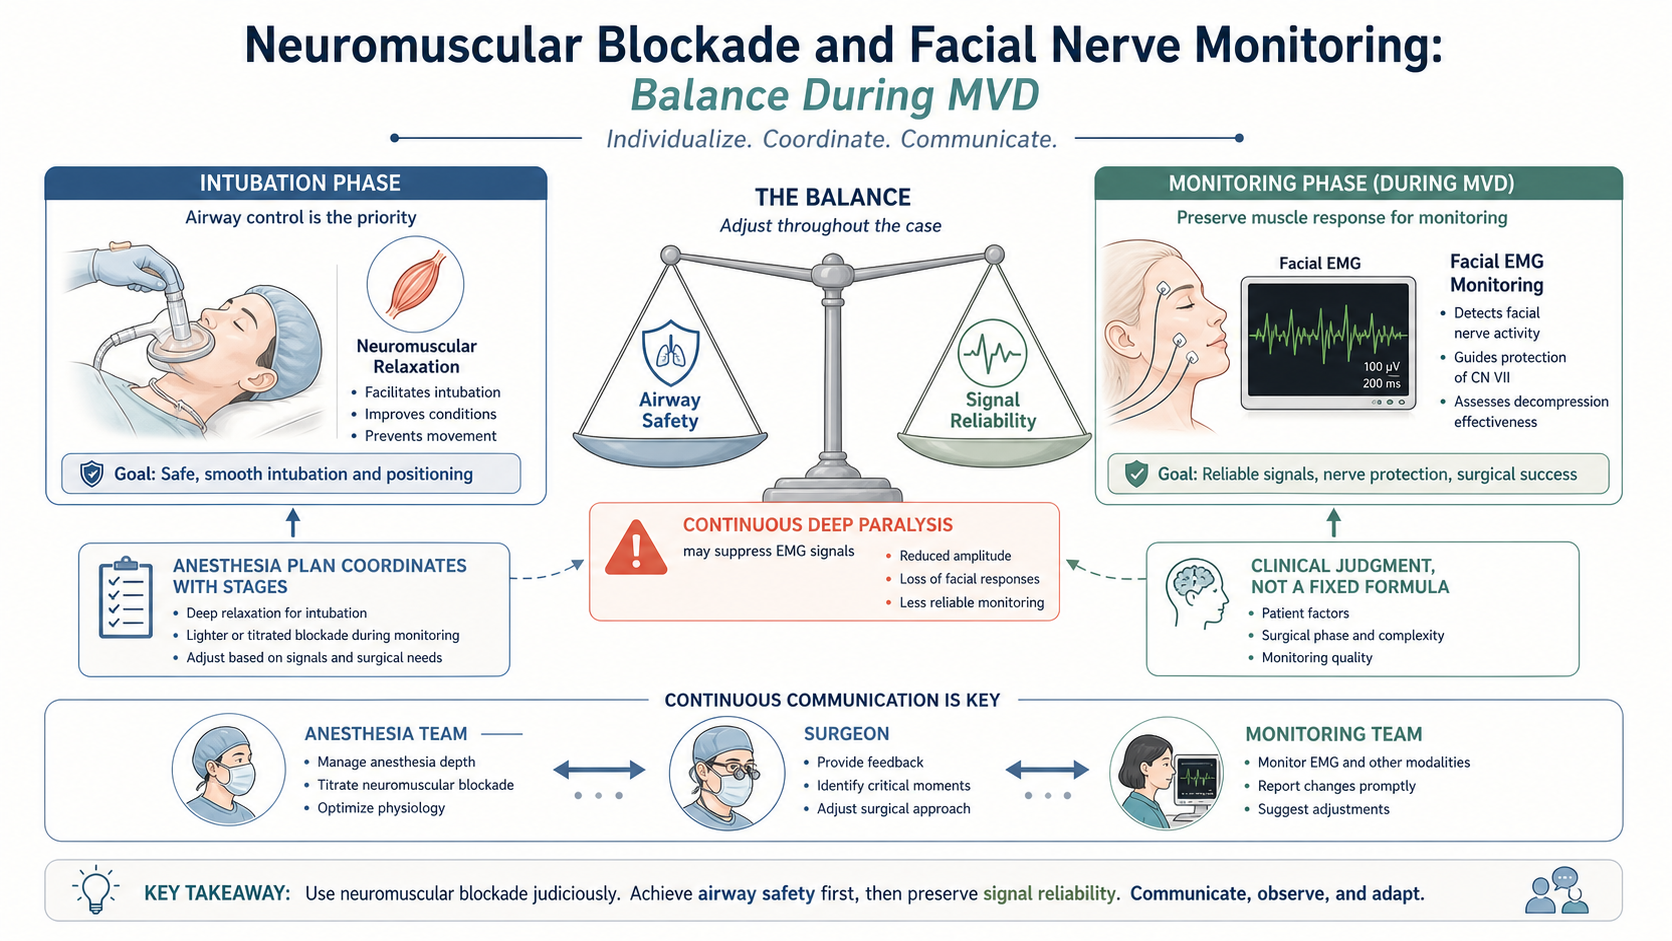

Neuromuscular blockade and facial nerve monitoring balance
这是本课件最关键图之一:安全气道与信号可靠性之间要动态平衡。 This is one of the key figures: airway safety and signal reliability must be balanced dynamically.
Hand-drawn anesthesia and signal balance
手绘图用于把复杂监测问题讲成一个“调音台”:睡眠、气道、通气、循环、神经信号都要协调。 The hand-drawn figure turns monitoring-friendly anesthesia into a mixing board: sleep, airway, ventilation, circulation, and nerve signals must be coordinated.

Intraoperative Priorities

术中麻醉关注点:显微手术里的稳定工程Intraoperative Priorities: Stability During Microsurgery

术中重点包括气道和通气、血流动力学、体位和压力点、眼保护、体温、液体、疼痛和恶心呕吐预防、神经监测沟通。学生可以把麻醉医生理解为“同时看多个系统反馈的人”。

Intraoperative priorities include airway and ventilation, hemodynamics, positioning and pressure points, eye protection, temperature, fluids, pain and PONV prevention, and communication around monitoring. The student can view the anesthesiologist as the person integrating multiple system feedback loops.
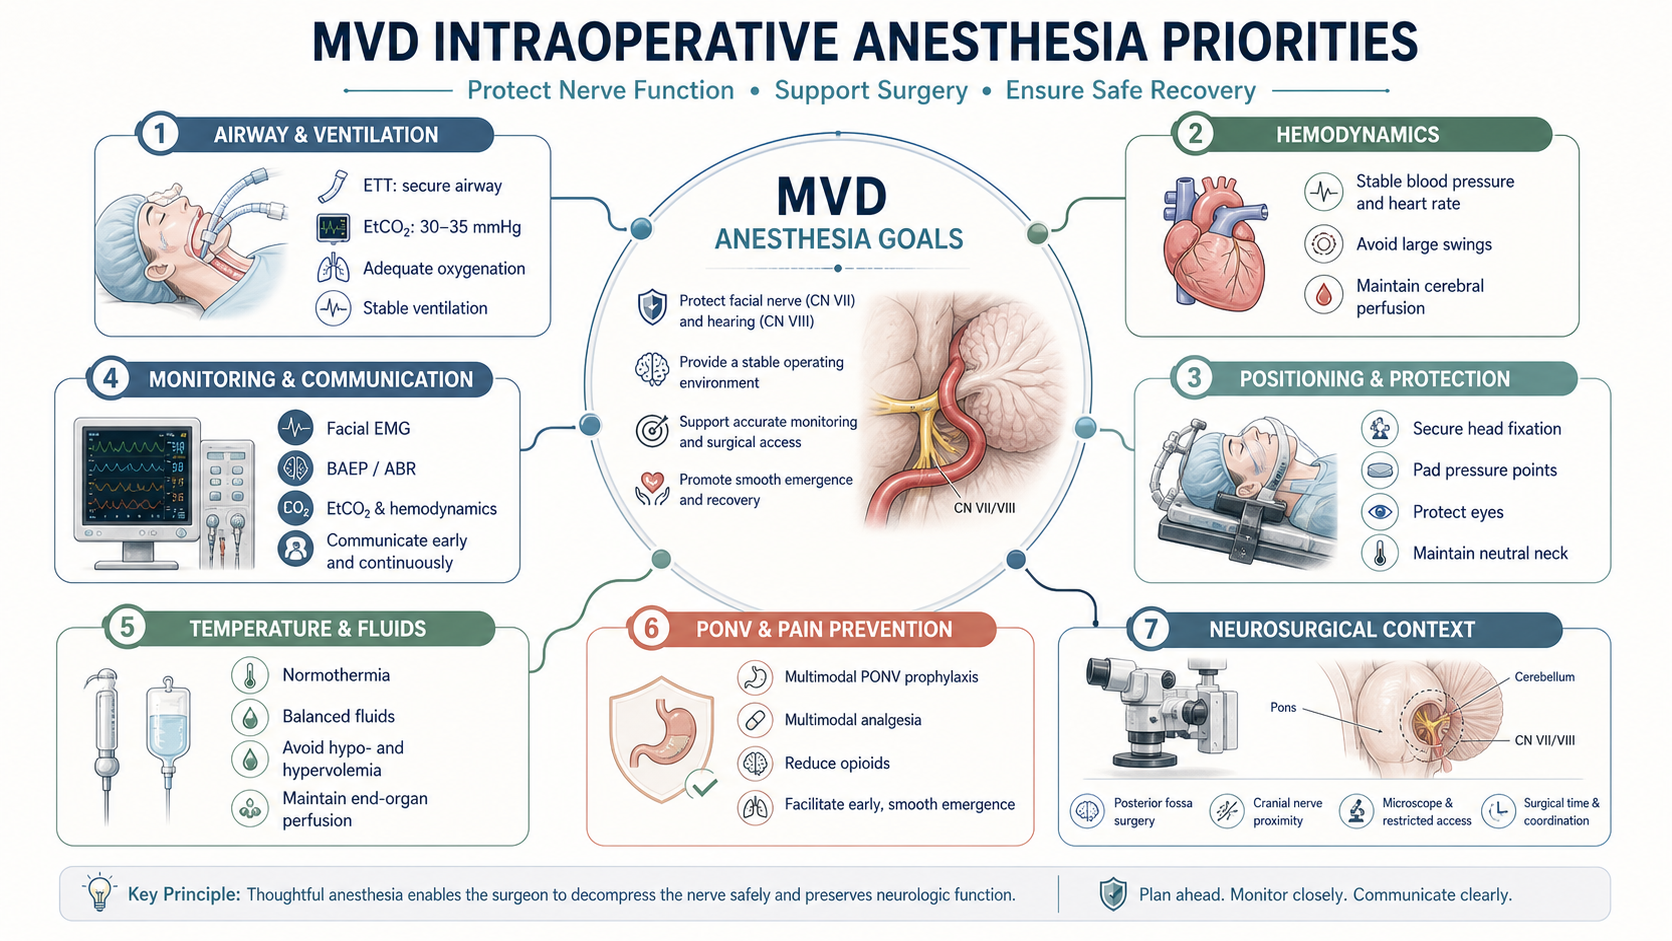
MVD intraoperative anesthesia priorities
这张矩阵适合作为术中观察清单的视觉版。 This matrix works as the visual version of an intraoperative observation checklist.

Observer Mode

学生现场观察清单Student Observation Checklist

Before induction 看身份核查、气道评估、静脉通路、基础生命体征、症状侧别和神经功能基线。 Observe identity check, airway assessment, IV access, baseline vitals, symptom side, and neurologic baseline.
Induction and airway 看预氧合、诱导、面罩通气、插管、EtCO2 确认、导管固定和眼保护。 Watch preoxygenation, induction, mask ventilation, intubation, EtCO2 confirmation, tube fixation, and eye protection.
Positioning 看头部固定、体位摆放、压力点保护、线路和导管是否安全。 Watch head fixation, positioning, pressure point protection, and safe lines and tubes.
Monitoring 听懂 Facial EMG、BAEP/ABR、信号质量和麻醉团队沟通。 Listen for Facial EMG, BAEP/ABR, signal quality, and anesthesia-team communication.
Maintenance 观察血压、心率、EtCO2、氧合、体温、液体和手术刺激的关系。 Connect blood pressure, heart rate, EtCO2, oxygenation, temperature, fluids, and surgical stimulation.
Emergence 看平稳苏醒、呼吸恢复、拔管准备、疼痛恶心处理和 PACU 交接。 Watch smooth emergence, return of breathing, extubation readiness, pain/PONV management, and PACU handoff.

Debrief

术后五问:把一次见习变成麻醉思维Five Post-Case Questions: Turn Observation into Anesthesia Reasoning

每台手术后用 2 分钟回答五个问题:为什么会面肌痉挛?MVD 解除的是什么冲突?为什么需要全麻插管?神经监测需要麻醉配合什么?苏醒后最先观察什么?

After the case, answer five questions in two minutes: Why does HFS happen? What conflict does MVD relieve? Why is GA with ETT useful? What does monitoring need from anesthesia? What should be checked first after emergence?

给学生的核心句:Anesthesia is not only putting the patient to sleep. It is protecting the brain, nerves, airway, and recovery. Core teaching line: Anesthesia is not only putting the patient to sleep. It is protecting the brain, nerves, airway, and recovery.
← 返回线下交流 · 课件馆